The STEP 1 extension supplies an important answer to a practical question: what happened after a successful course of semaglutide ended? In a 327-person exploratory follow-up group, substantial average weight regain occurred over the next year. But the familiar summary—that participants regained two-thirds of their lost weight—needs its denominator, population, and treatment context. It describes an average after both medication and structured lifestyle support stopped, not the percentage of people who regained everything.
Those distinctions matter when clinical evidence appears in advertising for ongoing care. The findings support taking maintenance seriously; they do not establish that every person needs indefinite medication, that a particular service prevents regain, or that a paid membership reproduces trial care. This analysis uses the accessible full STEP 1 extension article, indexed primary-report abstracts for the parent STEP 1 trial and two tirzepatide maintenance trials, and official FDA material. These evidence types answer different questions and should not be treated as interchangeable.
At a glance
- Who was followed
- The exploratory extension analysis included 327 treatment completers from selected sites, compared with 1,961 adults originally randomized in STEP 1.
- What stopped
- At week 68, study medication and the structured lifestyle intervention were withdrawn; follow-up continued for 52 more weeks.Sources: [2]
- Average weight trajectory
- The former semaglutide group lost 17.3% during treatment, regained 11.6 percentage points relative to starting weight, and remained 5.6% below baseline at week 120.Sources: [2]
- Individual results varied
- Among 197 former semaglutide participants with an onsite week-120 measurement, 95, or 48.2%, remained at least 5% below their starting weight.Sources: [2]
The original experiment tested medication plus lifestyle support
STEP 1 randomly assigned 1,961 adults without diabetes to once-weekly subcutaneous semaglutide or placebo, both alongside lifestyle intervention, for 68 weeks. Participants had a body mass index of at least 30, or at least 27 with a weight-related condition. Allocation was 2:1, with 1,306 assigned semaglutide and 655 placebo. The studied target dose was 2.4 mg, reached through 16 weeks of escalation; these doses identify the research arms, not instructions for use.
The parent trial's two primary outcomes were percentage change in body weight and the proportion losing at least 5%. Its main analysis assessed treatment assignment regardless of discontinuation or rescue interventions. Mean weight change was −14.9% with semaglutide versus −2.4% with placebo, an estimated difference of −12.4 percentage points, with a 95% confidence interval from −13.4 to −11.5.
Lifestyle support included counseling every four weeks about diet and physical activity. Thus, the experiment compared adding semaglutide with adding placebo within a shared support program. It did not compare medication with no care, and it did not test commercial membership packages. Novo Nordisk funded STEP 1 and the extension.
The extension was a selected completer study, not a new randomization
The extension followed people who had completed the assigned 68-week treatment and consented to further observation. Sites were selected in Canada, Germany, the United Kingdom, the United States, and Japan. In the latter two countries, selection favored sites with the highest recruitment in the main trial. Of 333 people entering the extension, 327 attended at least one eligible follow-up visit and entered its analysis set: 228 formerly assigned semaglutide and 99 placebo.
Their average age was 49 years, mean starting weight was 105.5 kg, and mean BMI was 37.6. Women accounted for 67.0% and White participants for 75.8%. Although baseline characteristics broadly resembled those of the original trial, completing treatment selects for experiences that may differ from those of people who discontinue early, including because of tolerability or other difficulties.
Crucially, participants were not newly randomized at week 68 to stop or continue semaglutide. Both original groups stopped study treatment. The extension therefore describes post-treatment trajectories in selected completers; it does not directly estimate the difference between continuing semaglutide and stopping it for another year.
STUDY DATA · GLP-1 Provider Brief
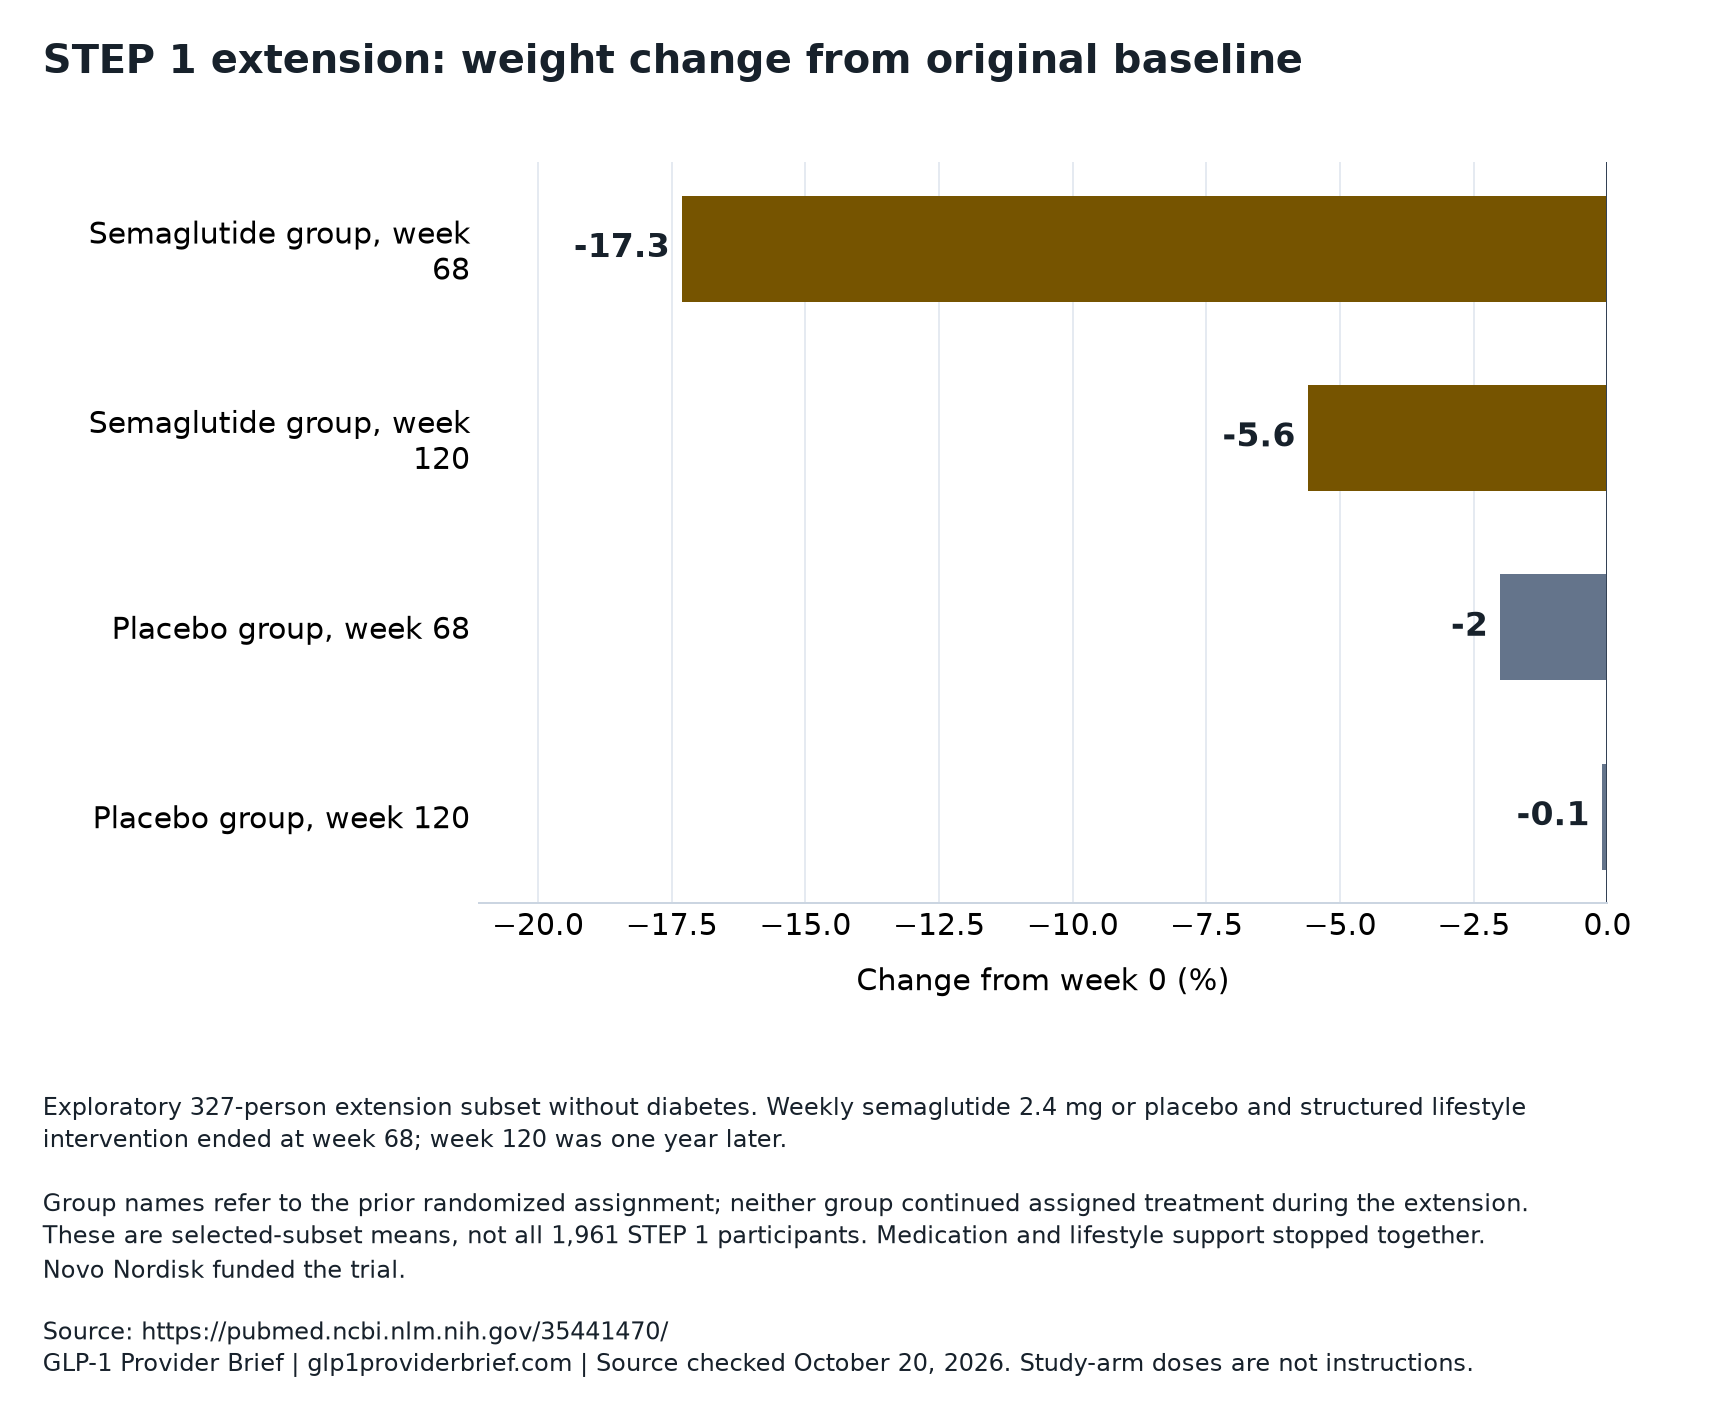
STEP 1 extension: weight change from original baseline
Exploratory 327-person extension subset without diabetes. Weekly semaglutide 2.4 mg or placebo and structured lifestyle intervention ended at week 68; week 120 was one year later.
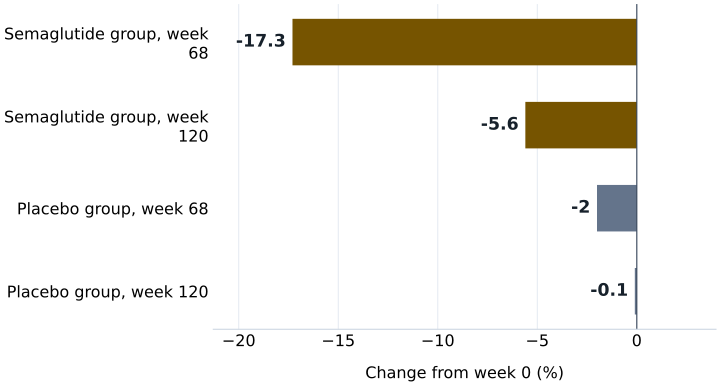
| Study group | Change from week 0 (%) |
|---|---|
| Semaglutide group, week 68 | -17.3 |
| Semaglutide group, week 120 | -5.6 |
| Placebo group, week 68 | -2 |
| Placebo group, week 120 | -0.1 |
Group names refer to the prior randomized assignment; neither group continued assigned treatment during the extension. These are selected-subset means, not all 1,961 STEP 1 participants. Medication and lifestyle support stopped together. Novo Nordisk funded the trial.
Original visualization of published aggregate data. No individual prediction or provider performance is represented. Original research ↗
Two-thirds regained is a ratio of average weight changes
Within the extension subset, observed mean loss through week 68 was 17.3% with semaglutide and 2.0% with placebo. Over the following year, the respective groups regained 11.6 and 1.9 percentage points of baseline weight. The former semaglutide group consequently remained an average 5.6% below its original weight, compared with 0.1% in the former placebo group.
The two-thirds description comes from dividing 11.6 by 17.3, which is approximately 0.67. It means roughly two-thirds of the group's previous average loss was regained. It does not mean two-thirds of participants returned to baseline, nor does it mean their body weight increased by 67%. Those would be different claims requiring different calculations.
An illustrative person starting at 100 kg makes the units clearer: a 17.3% loss corresponds to 17.3 kg, and an 11.6-percentage-point return corresponds to 11.6 kg on that original-weight scale. The published net loss is 5.6%, rather than the 5.7% obtained by subtracting rounded headline numbers; observed-data summaries should not be forced into exact arithmetic from rounded values.
| Reported measure | Former semaglutide group | Correct interpretation |
|---|---|---|
| Week 0–68 mean loss | 17.3% | Loss expressed relative to starting weight |
| Week 68–120 mean regain | 11.6 percentage points | Return on the starting-weight percentage scale |
| Fraction of prior average loss regained | About two-thirds | 11.6 divided by 17.3; not a count of participants |
| Week 0–120 mean net loss | 5.6% | Average weight remained below baseline |
| At least 5% below baseline at week 120 | 95 of 197; 48.2% | Observed proportion among onsite final-visit measurements |
Averages leave substantial differences between people
The standard deviation of initial semaglutide-associated loss was 9.3 percentage points; for subsequent regain it was 7.7, and for net loss at week 120 it was 8.9. A standard deviation describes variation among participants, not uncertainty around the group mean. These sizable spreads show why the average trajectory should not become an individual forecast.
Among former semaglutide participants with an onsite final measurement, 48.2% remained at least 5% below baseline, compared with 22.6% of former placebo participants. That finding establishes meaningful residual loss for many observed participants. It does not reveal how many maintained every kilogram lost, and it should not be recast as a guaranteed chance of success for a new patient.
Exploratory analyses also found that groups losing more during treatment tended to regain more afterward but still retained greater net losses. This is not contradictory: a larger initial loss leaves more weight available to regain. It also means that counting regained kilograms alone can obscure the amount of benefit remaining at follow-up.
Medication and structured support ended together
At week 68, the trial withdrew both study medication and its lifestyle intervention. The extension therefore cannot separate the contribution of medication withdrawal from the contribution of losing scheduled support. It would be equally mistaken to attribute the entire regain to either change. The observed result belongs to the combined transition that actually occurred.
Nor did the study establish that participants abandoned all weight-management behaviors. Participation in outside lifestyle programs was not recorded. No treatments were actively administered or prohibited during the extension, and some participants used obesity pharmacotherapy. Under investigators' classification, this included 9.2% of the former semaglutide arm and 6.1% of the former placebo arm.
Excluding pharmacotherapy users produced similar average net weight results, which makes such use an unlikely explanation for the overall pattern. Nevertheless, that sensitivity analysis does not create a randomized comparison of different maintenance strategies. Editorial interpretation: a service claiming that its coaching prevents post-medication regain would need evidence about that coaching program, not merely a citation showing regain after trial support ended.
Metabolic improvements partly receded, but not uniformly
Weight was not the only measurement. In the former semaglutide group, mean systolic blood pressure moved from 129 mmHg at baseline to 121 at week 68, then 131 at week 120. Mean diastolic pressure moved from 81 to 78 to 82 mmHg. These trajectories indicate that the treatment-period blood-pressure improvement was not sustained at the group level after withdrawal.
Other measures retained some improvement. Mean HbA1c, a measure of longer-term blood glucose, changed from 5.7% to 5.2% to 5.6%. Triglycerides changed from a geometric mean of 131.1 to 95.7 to 122.4 mg/dL. C-reactive protein, an inflammation marker, changed from 2.95 to 1.28 to 1.83 mg/L. These are measured risk factors, not proof of fewer heart attacks or other clinical events after stopping.
Among participants with prediabetes initially, 93.6% in the semaglutide group had normal-range HbA1c at week 68, falling to 43.3% at week 120; corresponding placebo proportions were 41.5% and 34.0%. These observed category changes do not establish permanent diabetes prevention. The study also cannot determine precisely how much reversal reflected weight regain versus removal of direct drug effects.
Missing measurements and exploratory analyses affect certainty
Although 312 of 333 entrants completed the extension, only 290 had onsite measurements at week 120: 197 formerly receiving semaglutide and 93 placebo. Another 22 completed final contact by telephone or email. Pandemic-related alternatives helped maintain contact, but self-reported measurements from remote visits were excluded from the analyses. Study completion and availability of measured final weight are therefore different denominators.
The off-treatment analyses used observed data, without a formal sample-size power calculation or a prespecified estimand defining a confirmatory treatment effect. Their headline regain figures were descriptive and accompanied by standard deviations, not confidence intervals establishing a randomized withdrawal effect. If missing onsite measurements were associated with different weight trajectories, the observed averages could differ from those for everyone enrolled.
For the separate comparison during the initial 68 weeks, the extension subset's modeled semaglutide–placebo difference was −15.3 percentage points, with a 95% confidence interval of −17.3 to −13.3. That exceeds the parent trial's −12.4-point difference, consistent with the subset's completer selection. Neither estimate supplies the missing counterfactual of continued semaglutide during the extension.
Randomized maintenance trials ask different questions
The SURMOUNT-4 withdrawal analysis offers a useful design contrast, but it studied tirzepatide, not semaglutide. After 36 weeks of open-label weekly subcutaneous tirzepatide at a maximum tolerated 10 or 15 mg, 670 participants were randomized to continue or switch to placebo for 52 weeks. Diet and physical-activity intervention continued. The primary endpoint measured percentage weight change from that new randomization point.
Participants had initially lost 20.9% on average. Thereafter, mean change was −5.5% with continued tirzepatide versus +14.0% with placebo; the estimated between-group difference was −19.4 percentage points, with a 95% confidence interval of −21.2 to −17.7. Unlike STEP 1's extension, this directly compared continuation with withdrawal. Its different medication, selection process, support, and percentage denominator prevent a simple numerical cross-trial comparison.
SURMOUNT-MAINTAIN randomized 378 participants after 60 weeks of tirzepatide to continued maximum tolerated dosing, 5 mg, or placebo. Estimated baseline-to-week-112 changes were −21.9%, −16.6%, and −9.9%, respectively, with reported 95% confidence intervals of −23.5 to −20.3, −18.0 to −15.1, and −11.1 to −8.8. Rescue treatment and its analysis assumptions matter. These are maintenance comparisons, not the direct medication comparison discussed in our head-to-head evidence guide.
Safety and formulation cannot be inferred from weight maintenance
The STEP 1 extension did not systematically collect adverse events. It therefore cannot establish the safety of withdrawal or characterize every symptom after treatment ended. In the parent STEP 1 report, nausea and diarrhea were the most common semaglutide adverse events, generally transient and mild to moderate. Gastrointestinal events nevertheless caused discontinuation in 59 semaglutide participants, or 4.5%, versus five placebo participants, or 0.8%.
The tirzepatide maintenance abstracts likewise reported predominantly mild-to-moderate gastrointestinal events. SURMOUNT-4 reported them more commonly with tirzepatide than placebo; SURMOUNT-MAINTAIN reported that they occurred mostly during escalation. These observations matter when interpreting continued-treatment benefits: maintaining weight loss is one outcome, not a blanket finding of safety or tolerability for every person.
Evidence also remains formulation-specific. FDA states that compounded drugs are not approved or reviewed before marketing for safety, effectiveness, or quality, and identifies dosing errors and semaglutide salt concerns. Reports alone do not establish event rates or causation. Our product-terms guide helps distinguish the product named in an agreement from the injected formulation studied here; the trial does not establish equivalence for compounded preparations or oral routes.
Clinical maintenance evidence is not a contract requirement
A defensible service statement would describe substantial average regain after withdrawal in the studied population while acknowledging residual loss and variation. Claims that everyone regains everything, that lifelong treatment is proven necessary for every individual, or that one provider guarantees maintenance go beyond these findings. One year of observation cannot establish every person's lifetime trajectory.
Editorial interpretation: evidence supporting ongoing clinical planning does not establish a minimum subscription term, an automatic-renewal requirement, or a refund condition. Those require their own written documentation. The billing-commitments guide separates payment schedules from contractual duration, while the evidence-boundaries guide explains why clear terms do not themselves prove clinical outcomes.
For documentary comparison, the CoreAge Rx review and Mochi Health review can be used to check which contract questions need written answers. These links do not imply that either provider offers the studied product or reproduces trial care. A provider-specific maintenance claim would need matching evidence about its actual population, formulation, intervention, follow-up, and missing outcomes.
| Claim | What this evidence supports | Documentation still needed |
|---|---|---|
| Regain can follow treatment withdrawal | Substantial average regain after medication and trial lifestyle support ended | Accurate population, time frame, and outcome description |
| Everyone returns to starting weight | Not supported; average residual loss and varied outcomes remained | Individual-outcome evidence, not a group-average ratio |
| Our program prevents regain | Not tested in STEP 1's extension | Program-specific comparative outcome data |
| A long subscription is medically required | No contractual duration was studied | Separate clinical rationale and explicit contract terms |
| Another formulation delivers the same results | Not established by these trials | Evidence specific to that product and route |
Questions & answers
Does two-thirds regained mean two-thirds of participants regained all their weight?
No. It is the ratio of average regain to average prior loss: 11.6 divided by 17.3. It is not a proportion of participants. At the final onsite visit, 48.2% of the former semaglutide group still had at least 5% weight loss from baseline, although that does not mean they maintained all of their initial loss.
Why is the extension's 17.3% loss larger than STEP 1's familiar 14.9%?
The figures describe different analysis populations and methods. The extension selected people who completed 68 weeks of treatment and reported their observed loss. The parent trial's primary analysis included the randomized population under an approach accounting for discontinuation and rescue interventions. Substituting the completer result for the parent trial estimate makes expected benefit look larger.
Could continued lifestyle support have changed the regain?
Possibly, but the extension cannot quantify that contribution because structured support and medication ended together. It did not randomize people to continued versus discontinued counseling, and outside lifestyle-program participation was not recorded. The design supports describing what followed the combined withdrawal, not assigning an exact share of regain to each change.
Does this prove medication must continue forever?
No. The findings support the importance of maintenance treatment for many people, but the extension observed only one year after withdrawal and had no continued-semaglutide comparison. It did not test lifetime treatment, establish a universal duration, or resolve whether the slowing of regain near the end would become a lasting plateau.
Do newer dose-reduction results establish a semaglutide taper?
No. SURMOUNT-MAINTAIN studied specific tirzepatide maintenance arms after a 60-week lead-in, with rescue treatment available under defined conditions. Its lower-dose arm provides evidence about that trial strategy, not a semaglutide tapering protocol or an individualized stopping plan. Different drugs and study designs should not be treated as interchangeable instructions.
Our assessment
The STEP 1 extension provides credible descriptive evidence of substantial average regain after semaglutide and structured lifestyle support ended, alongside partial persistence of weight and metabolic improvements. Its strongest implication is that maintenance deserves deliberate clinical attention. Its weakest use is as a universal prediction or a justification for a provider's commercial guarantee. Selected completers, simultaneous withdrawal of two interventions, missing onsite measurements, and a one-year horizon constrain what can be concluded. Randomized tirzepatide maintenance trials strengthen the broader case for continued-treatment benefits, but do not erase those design differences or validate a particular service contract.
Sources & documentation
Scientific and official sources consulted October 20, 2026. Study findings apply to the populations, products and time periods described; they are not provider outcome data.
- Once-Weekly Semaglutide in Adults with Overweight or Obesity. ↗
- Weight regain and cardiometabolic effects after withdrawal of semaglutide: The STEP 1 trial extension. ↗
- Continued Treatment With Tirzepatide for Maintenance of Weight Reduction in Adults With Obesity: The SURMOUNT-4 Randomized Clinical Trial. ↗
- Tirzepatide for maintenance of bodyweight reduction in people with obesity in the USA (SURMOUNT-MAINTAIN): a multicentre, double-blind, randomised, placebo-controlled trial. ↗
- FDA concerns about unapproved GLP-1 drugs ↗